
By E-commerce 4 Internet Marketers Editorial
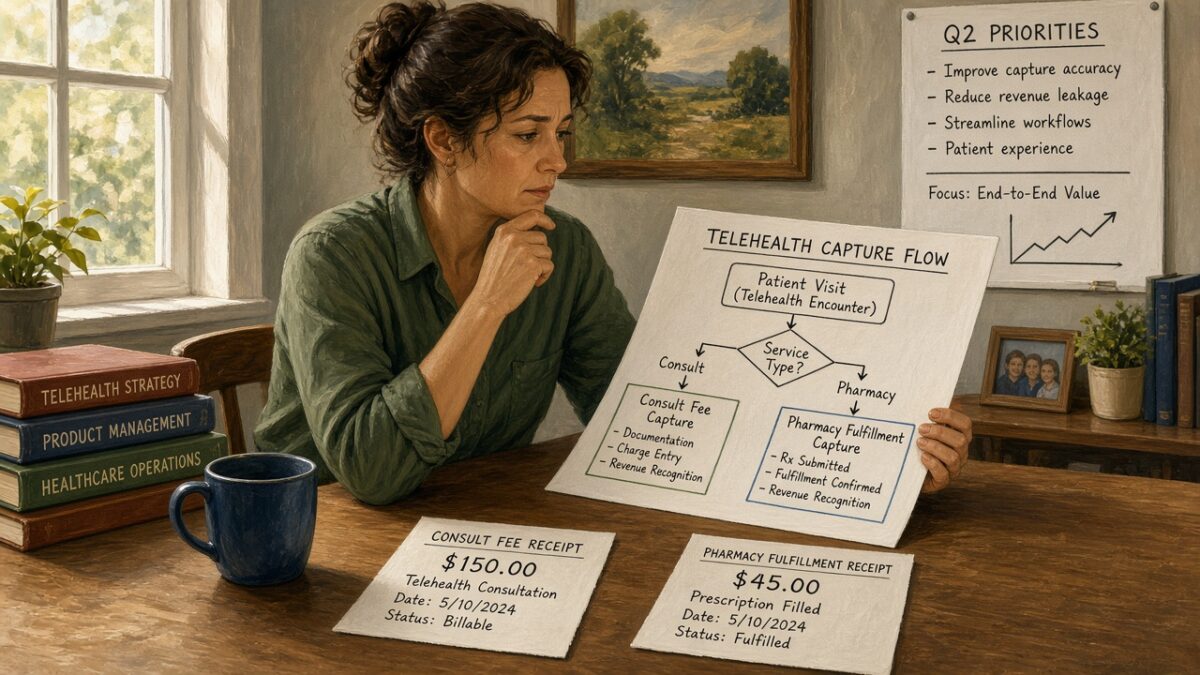
Explainer. Bundling a telehealth consult fee and a pharmacy fulfillment charge into one opaque card payment is a common dispute and ops failure mode for website owners and developers who sell regulated or high-risk telehealth catalogs. Cardholders see one amount and one merchant name. Support teams then cannot map a refund, void, or chargeback to consult-only, pharmacy-only, or both. This article maps a checkout architecture that keeps consult payment, prescription (Rx) approval, and pharmacy capture as separate, auditable money events, using verified processor and network documentation for authorization-capture windows and statement descriptors. Related marketing context comes from the U.S. Food and Drug Administration (FDA) page FDA to Telehealth Companies: What to Know When Promoting Compounded Drugs (content current as of 06/15/2026).
Primary payment sources are Stripe Place a hold on a payment method, Stripe Place an extended hold on an online card payment, Stripe Statement descriptors, Authorize.net Payment Transactions, and Visa's Standards Reminders for Merchant Name / Descriptor Field. This is not legal, clinical, pharmacy, or underwriting advice. Confirm product, state, and acquirer rules with counsel.
Why one bundled charge breaks audits
Telehealth carts often price three different commercial events as if they were one SKU. Event A is the consult or visit fee owed when a clinician encounter is booked or completed. Event B is a conditional pharmacy amount that should settle only after an Rx is issued and a pharmacy can fulfill. Event C is any membership, lab, or add-on that may recur on a different schedule. When checkout collapses A plus B into a single authCapture or automatic capture, the merchant ledger, the card statement, and the dispute record all lose the join key that auditors need.
That loss shows up in three operational places. First, statement recognition fails when the descriptor names a consumer brand while the amount mixes clinical and pharmacy dollars. Visa's merchant-name reminders state that correct descriptors increase recognition and reduce disputes, and that the merchant name must be the name the cardholder primarily recognizes, displayed on the ecommerce site, and used consistently on the receipt, authorization, clearing, and dispute records. Second, refund math fails when a denied Rx should reverse only the pharmacy portion, or when a cancelled consult should reverse only the consult portion. Third, marketing and payment risk collide when website copy implies the telehealth brand is the compounder or that a compounded product is FDA-approved. FDA's telehealth compounding promotion page warns against branding that falsely implies the telehealth company is the compounder, against calling compounded drugs generics or FDA-approved, and against claiming sourcing from an "FDA-approved" or "FDA-licensed" pharmacy. Checkout money design cannot fix false promotion claims, but it should not amplify them with a single unexplained charge labeled as both visit and medication.
Design goal. Three money states, one order graph
Treat the patient journey as an order graph with explicit payment nodes rather than a single cart total.
- Consult node. Price, authorize, and usually capture (or invoice) when the consult service is actually owed under your posted terms. Prefer an immediate settle for the consult when the service is delivered or non-refundable under clearly disclosed terms. Store
consult_payment_id, amount, capture timestamp, and descriptor suffix used. - Rx decision node. Persist clinician decision outcomes (
approved,denied,needs_info) with timestamps and actor IDs. Do not treat a marketing quiz pass as an Rx. Payment automation should listen only to the clinical system's verified status webhook or signed callback. - Pharmacy node. Authorize the pharmacy amount only when you are ready to fulfill, or place a hold earlier only if your processor window and MCC allow it and you can void cleanly on denial. Capture only after the pharmacy confirms it can ship or dispense. Store
pharmacy_payment_idseparately from the consult payment ID.
The engineering invariant is simple. Every refund, void, and chargeback must point at exactly one payment node (or an explicit multi-node reversal list), never at a blended total with no child IDs.
Pattern A. Two separate captures (consult now, pharmacy later)
When it fits. Consult is due at booking or after the visit. Pharmacy dollars are unknown or should not settle until Rx approval and fulfillment readiness. Cardholders should see two recognizable charges, or one consult charge and a later pharmacy charge.
Stripe shape. Create one PaymentIntent for the consult with default or automatic capture (or manual capture if you still need a short hold). Create a second PaymentIntent for the pharmacy amount later, with capture_method=manual only if you must authorize before fulfillment, then capture when ready. Stripe documents that setting capture_method to manual authorizes without capturing, moves the intent to requires_capture, and requires capture before the authorization expires. For card-not-present customer-initiated transactions, Stripe's published validity table lists Visa at 7 days, Mastercard at 7 days, American Express at 7 days, and Discover at 7 days. Rely on payment_method_details.card.capture_before on the Charge rather than hard-coding brand lore in application code. Cancel the PaymentIntent if the Rx is denied or fulfillment cannot proceed.
Authorize.net shape. Use authCaptureTransaction for the consult when you intend to settle immediately. For the pharmacy path that needs a hold, use authOnlyTransaction, then priorAuthCaptureTransaction with refTransId when fulfillment is ready, or voidTransaction if the Rx is denied before settlement. Authorize.net states that Authorization Only transactions that are not captured within 30 days expire on the gateway and are no longer available for settlement, that only one Prior Authorization Capture may be submitted against an Authorization Only transaction, and that capture amount must be less than or equal to the original authorized amount. After settlement, use refundTransaction rather than void.
Descriptor practice. Give each PaymentIntent or gateway transaction a cardholder-recognizable suffix that separates CONSULT from RX or PHARM within the 22-character statement-descriptor limits documented by Stripe (complete descriptor 5 to 22 characters; card payments use a Dashboard prefix plus statement_descriptor_suffix, joined with * and a space). Example pattern when the prefix is short enough. BRAND* CONSULT and BRAND* RXSHIP. Do not invent network-mandated telehealth wording. Keep the DBA consistent with the site name Visa expects cardholders to recognize, and keep spelling consistent across receipt, auth, and clearing.
Pattern B. Single pharmacy authorization held until Rx approval
When it fits. The consult is free, already settled offline, or billed as a membership, and the only card event is medication fulfillment. You still want an auth before pharmacy work starts, then capture or void based on Rx outcome.
Mechanics. Authorize the expected pharmacy amount with manual capture (Stripe) or Authorization Only (Authorize.net). Gate capture on the Rx-approved plus pharmacy-ready signal. On denial, cancel or void rather than capturing and refunding when the transaction is still unsettled. Authorize.net notes that a void cancels before settlement, while a credit refunds after settlement, and that issuer holds may remain briefly after a void until the issuer expires them.
Window risk. Do not assume a multi-week clinical review fits inside a standard online card authorization. Stripe's extended-authorization docs state that extended holds can reach up to about 30 days depending on brand and category, require capture_method=manual plus a request flag such as request_extended_authorization=if_available, and still require reading capture_before. Those docs also state that for Visa "other merchant categories," the extended window does not apply to transactions related to healthcare, bill payment, or debt repayment (among other limits). Telehealth operators should therefore treat extended authorization as MCC- and network-dependent, not as a guaranteed clinical SLA buffer. If the review routinely exceeds the available hold, collect a new customer-initiated authorization at fulfillment time instead of stretching an expired hold.
Pattern C. What not to do with partial capture of a blended total
Merchants sometimes authorize consult-plus-pharmacy as one amount, then partially capture "only the consult" or "only the pharmacy." That is fragile for auditability.
Stripe documents that for most payments you can perform only one capture on an authorized payment, that a partial capture releases the remainder, and that you generally cannot capture the difference later on the same authorization (save the payment method and create a future payment instead). Authorize.net similarly allows a single Prior Authorization Capture at an amount less than or equal to the original Authorization Only amount. A blended auth therefore forces an awkward choice. Capture the full blend and refund pieces later, or partial-capture one piece and lose the rest of the hold. Neither choice preserves clean consult-versus-pharmacy payment IDs as well as two intentional payment nodes.
If you must show a combined cart total for UX, still create separate server-side payment intents or gateway transactions per node at submit time. Display math can aggregate. Settlement IDs should not.
Statement descriptors that survive support tickets
Visa's December 2020 standards reminder (republished with corrected Rules IDs) requires the merchant name to be the name primarily used with customers, displayed on the ecommerce site, and used consistently (including spelling) on the cardholder receipt, authorization request, clearing record, and dispute records. It states the name must not be modified periodically to mask identity from compliance programs. It also prohibits stuffing the descriptor with marketing statements unrelated to the transaction, and it reserves asterisk-separated formats for defined acceptance entities such as payment facilitators and sponsored merchants rather than arbitrary third parties.
Stripe's statement-descriptor guide adds implementable constraints for Stripe-processed cards. Complete descriptors need Latin characters, length 5 to 22 inclusive, at least one letter, no < > \ ' " * in the value you supply, reflection of the DBA, and more than a single common term or bare URL unless the URL clearly describes the transaction. Dynamic suffixes are card-only and concatenate as PREFIX* SUFFIX toward the 22-character network limit.
For telehealth, practical mapping for developers.
- Keep one stable DBA prefix that matches the storefront brand cardholders see.
- Encode the money node in the suffix (
CONSULT,VISIT,RX,PHARM,LAB) rather than a campaign slogan. - Persist the exact descriptor string sent on each payment row in your OMS.
- Show the same labels on the order confirmation email and customer portal so the statement and the inbox match.
- If a pharmacy partner settles on its own MID, do not pretend those charges are yours in support macros. Route the customer to the descriptor they actually see.
Clear descriptors reduce "what is this charge?" tickets. They do not legalize misleading product claims. Keep FDA promotion rules on a separate compliance track from MID descriptor configuration.
Refunds, voids, and chargeback evidence
Build refund APIs around payment-node IDs.
- Consult cancelled before service, unsettled. Void or cancel the consult authorization.
- Consult cancelled after settlement. Refund the consult payment ID only.
- Rx denied, pharmacy auth still open. Void or cancel the pharmacy authorization. Do not touch a settled consult unless your posted terms say the consult is also refundable.
- Pharmacy cannot fulfill after capture. Refund the pharmacy payment ID. Attach pharmacy decline or out-of-stock evidence to the order.
- Cardholder disputes a blended legacy charge. Export the order graph, both descriptors, Rx timestamps, fulfillment scans, and customer communications. Expect a harder fight than with node-scoped charges.
Authorize.net's transaction model is explicit that voids apply before settlement and credits apply after, with credits allowed up to the original capture amount (default refund window cited as within 180 days of settlement in Authorize.net's Payment Transactions documentation). Stripe's hold guide notes that some issuer statements do not clearly distinguish authorizations from captured payments, which is another reason to message customers when a hold is placed versus when funds settle.
Checkout UX that matches the money graph
Second person appears here only where the implementation instruction needs it.
- Label line items honestly. Show "Clinician consult" and "Medication fulfillment if prescribed" as separate lines with separate prices, even if the second line is estimated.
- Disclose conditionality. State that pharmacy capture or a second charge occurs only if a prescription is issued and the pharmacy can fulfill. Do not invent clinical criteria in the disclosure. Point to the care team's process.
- Avoid implying drug approval status in the payment step. FDA's telehealth compounding page is about promotion claims, not checkout buttons, but a pay wall that says "FDA-approved medication" for a compounded SKU recreates the exact failure mode that page warns about.
- Confirm after each money event. Send a consult receipt when the consult settles. Send a separate pharmacy receipt when pharmacy captures. Reuse the descriptor language.
- Block double submits. Use idempotency keys per node (
consult:{order_id},pharmacy:{order_id}:{rx_id}) so retries do not create duplicate captures. - Membership and autoship. If a subscription funds ongoing pharmacy shipments, keep the subscription's statement descriptor and invoice line items as explicit as one-time pharmacy captures. Do not hide medication renewals inside an unlabeled membership charge without clear invoice lines.
Implementation checklist for website owners and developers
- Model
Order,ConsultPayment,RxDecision, andPharmacyPaymentas separate records with foreign keys. - Never settle pharmacy dollars on the same gateway transaction ID as the consult when Rx approval is still pending.
- Choose Pattern A (two captures) by default when both consult and pharmacy are carded.
- Use Authorization Only / manual capture only when the hold window covers your real Rx turnaround. Prefer a fresh CIT authorization at fulfillment if windows are tight.
- Read Stripe
capture_before(or gateway expiry) into a worker that voids or re-auths before silent expiry. - Configure descriptor prefixes in the processor Dashboard to the public DBA. Pass node-specific suffixes per payment.
- Write refund services that require a payment-node ID and a reason code (
consult_cancel,rx_denied,pharmacy_unable,duplicate). - Log descriptor, auth code, capture ID, amount, and Rx decision ID together for dispute packets.
- Keep marketing claim review (FDA compounded-drug promotion reminders) on a release checklist separate from payment release.
- Have counsel and the acquirer review MCC, healthcare authorization practices, and any sponsored-merchant or payment-facilitator descriptor formats before launch.
What this explainer does not invent
This article does not invent federal or state clinical standards for telehealth exams, prescribing, pharmacy licensure, compounding eligibility, or drug approval pathways. It does not invent card-network specialty bulletins, MATCH or registration program text, or processor pricing. FDA material is limited to the agency's published telehealth compounding promotion reminders dated as current of 06/15/2026. Authorization timing and capture rules are limited to Stripe and Authorize.net primary docs fetched for this draft. Descriptor consistency rules are limited to Visa's published merchant-name reminder PDF and Stripe's statement-descriptor requirements. Extended-authorization availability, including Stripe's documented healthcare-related limits for certain Visa extended windows, must be confirmed against live processor responses (capture_before, extended-auth status) rather than assumed. Acquirer packets and state pharmacy rules override blog-level summaries. This is not legal advice.